The question
Does amyloid build-up start Alzheimer's disease and trigger the damage that follows?
This is the specific idea being tested.
Does amyloid build-up start Alzheimer's disease and trigger the damage that follows?
What you need to knowAmyloid matters, but a model with several interacting causes fits better than an amyloid-first explanation.Relative explanatory fit: Alternative ranked ahead
Why the alternative fits better: Some people have substantial amyloid deposits but relatively little tau damage or delayed symptoms. Amyloid alone does not fully explain this.
Claim assessed: Aβ accumulation is the primary upstream driver of Alzheimer's disease, initiating tau pathology, synaptic failure and progressive neurodegeneration in familial and sporadic disease.
Finding: Scope-matched SC4 returns Γ for primary initiation/generalization; SC5 separately returns Ε for early clinical contribution. Human genetics and clinical perturbations are considered together and are not re-capped as mere association. Their convergence supports bounded amyloid contribution, while sole/primary initiation and exact pathogenic-species mediation remain unresolved.
Evidence scope: 56 examined primary reports; publication cutoff 2026-10-04. Bounded critical review, not exhaustive systematic search.
The grade applies to the stated claim. Model rankings and individual subclaim grades remain separate from the overall causal-evidence grade.
Full scientific assessment and references · Scorecard (JSON) · Review source (Markdown)
THE MAIN FINDING
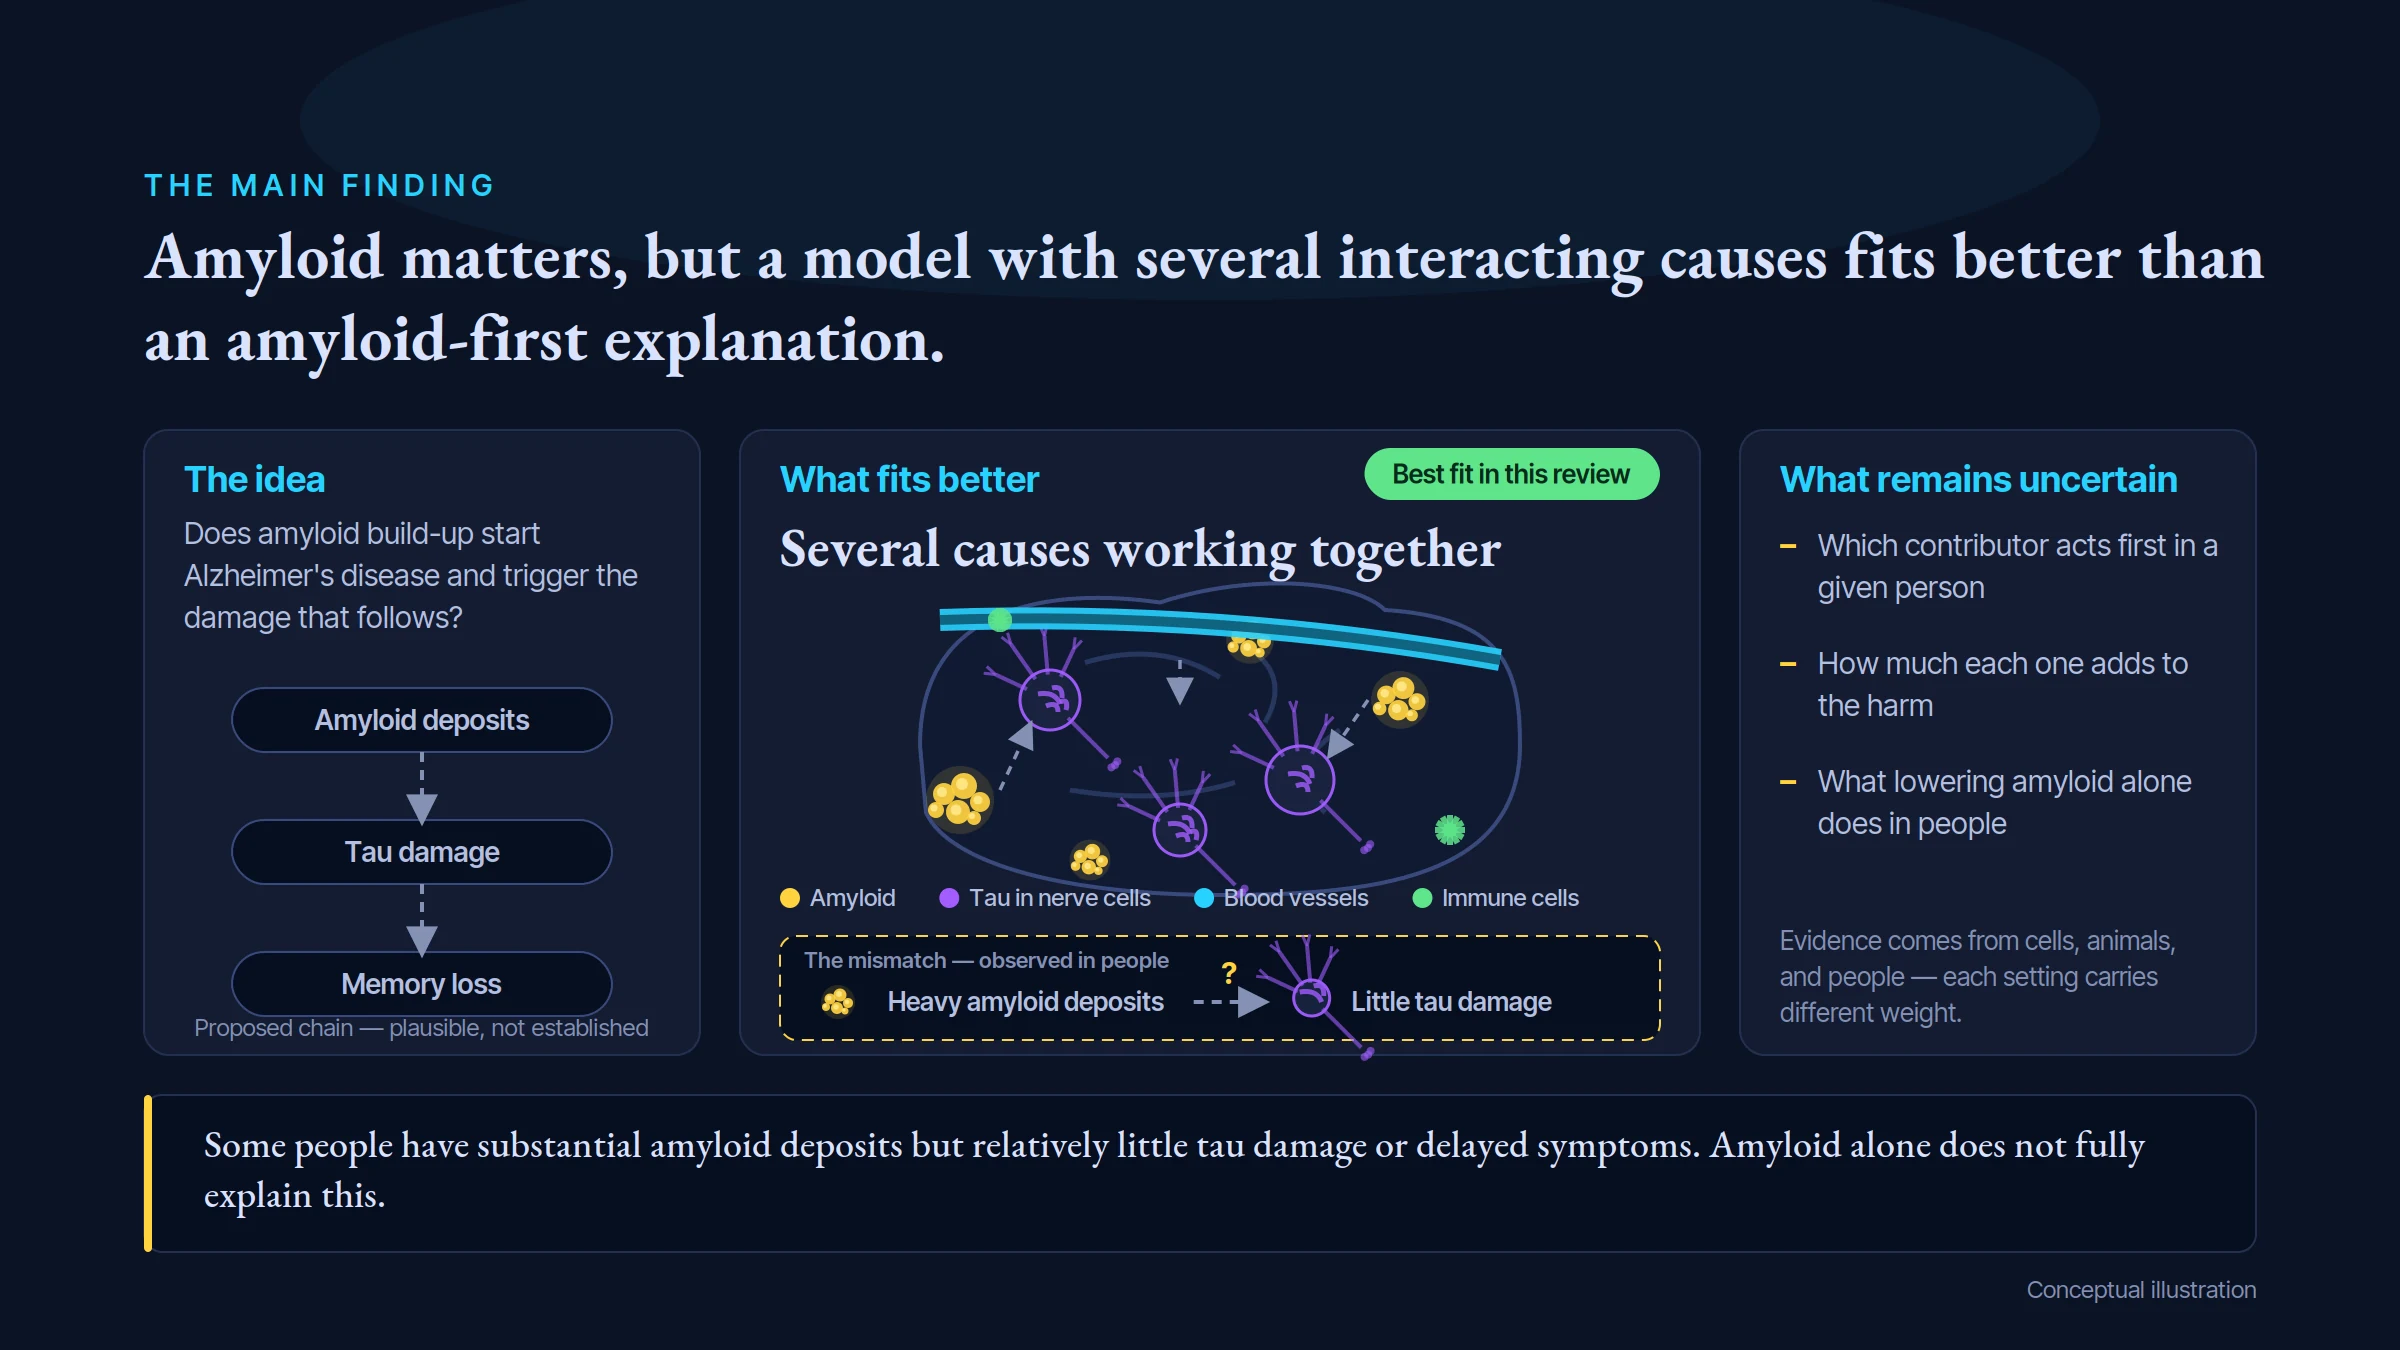
Amyloid matters, but a model with several interacting causes fits better than an amyloid-first explanation.
The idea
Does amyloid build-up start Alzheimer's disease and trigger the damage that follows?
Amyloid deposits
Tau damage
Memory loss
Proposed chain — plausible, not established
What fits better
Several causes working together
Best fit in this review
Amyloid
Tau in nerve cells
Blood vessels
Immune cells
The mismatch — observed in people
Heavy amyloid deposits
Little tau damage
What remains uncertain
Which contributor acts first in a given person
How much each one adds to the harm
What lowering amyloid alone does in people
Evidence comes from cells, animals, and people — each setting carries different weight.
Some people have substantial amyloid deposits but relatively little tau damage or delayed symptoms. Amyloid alone does not fully explain this.
Conceptual illustration
This is the specific idea being tested.
Some people have substantial amyloid deposits but relatively little tau damage or delayed symptoms. Amyloid alone does not fully explain this.
A higher rank means a better fit to the evidence in this comparison. It does not prove every part of the leading explanation.
The reviewed hypothesis ranks 2 among 5 models compared; 1 alternative model(s) hold first rank for this stated claim.
Claim under review: rank 2 among 5 compared models.
Leading explanation: Heterogeneous multi-hit AD.
Position in this comparison: Next after leading rank.
The causal grade asks how well the stated causal claim is established. This comparison asks which of the assessed explanations fits the reviewed findings better. A leading explanation can remain unproven. Models can overlap or include the tested mechanism; an alternative ahead does not make that mechanism irrelevant. These ordinal ranks apply within this review; they do not measure the size of a difference or rank scientific strength across topics.

TWO EXPLANATIONS, COMPARED
A · The idea under review
Does amyloid build-up start Alzheimer's disease and trigger the damage that follows?
Proposed chain
Amyloid build-up
Tau damage
Memory loss
Each arrow is a proposal, not a proven step.
Some people have substantial amyloid deposits but relatively little tau damage or delayed symptoms. Amyloid alone does not fully explain this.
B · Leading explanation
Several causes working together
Another explanation fits better
Interacting contributors (proposed links are dashed)
A better fit is not proof of every part of the explanation.
These explanations can overlap.
Conceptual illustration
Plausible, not established for the stated claim.
Some people have substantial amyloid deposits but relatively little tau damage or delayed symptoms. Amyloid alone does not fully explain this.
These explanations can overlap. Ranking their fit to the evidence is separate from deciding how firmly a cause has been established.
Rank 1: Heterogeneous multi-hit AD — Multiple interacting initiating and amplifying pathways produce AD trajectories, with context-dependent amyloid contribution.
Rank 2: Amyloid-primary cascade — Amyloid accumulation is the primary initiating driver upstream of tau and clinical injury across AD.
Rank 3: Tau-primary/selective vulnerability — Tau-associated injury and neuronal vulnerability determine degeneration; amyloid facilitates rather than universally initiates it.
Rank 4: Vascular/clearance failure — Vascular and clearance disturbances drive some injury and amyloid retention.
Rank 5: Inflammatory initiation — Glial innate pathways initiate injury and drive amyloid/tau downstream.
Evidence rating: Γ · Moderate confidence. How the evidence was assessed.
Some people have substantial amyloid deposits but relatively little tau damage or delayed symptoms. Amyloid alone does not fully explain this.
For human health, the evidence supports discussing amyloid-targeting treatment as one option for some carefully assessed people with early Alzheimer's disease. In the trials reviewed, amyloid removal slowed decline modestly for some participants; it did not restore lost memory, prove prevention, or show that amyloid alone explains disease. The result keeps attention on amyloid while also supporting research on tau, blood-vessel disease, inflammation, and other contributors.
Look for the proposed factor and the outcome, in the people or systems covered by the claim.
Several causes working together. Some people have substantial amyloid deposits but relatively little tau damage or delayed symptoms. Amyloid alone does not fully explain this.
Measure amyloid, tau, blood-vessel health and memory together to test which changes drive later damage.
These illustrations show the key questions tested in the review. They are conceptual drawings, not microscope images or experimental results.
WHAT WOULD MAKE THE ANSWER CLEARER
A research question
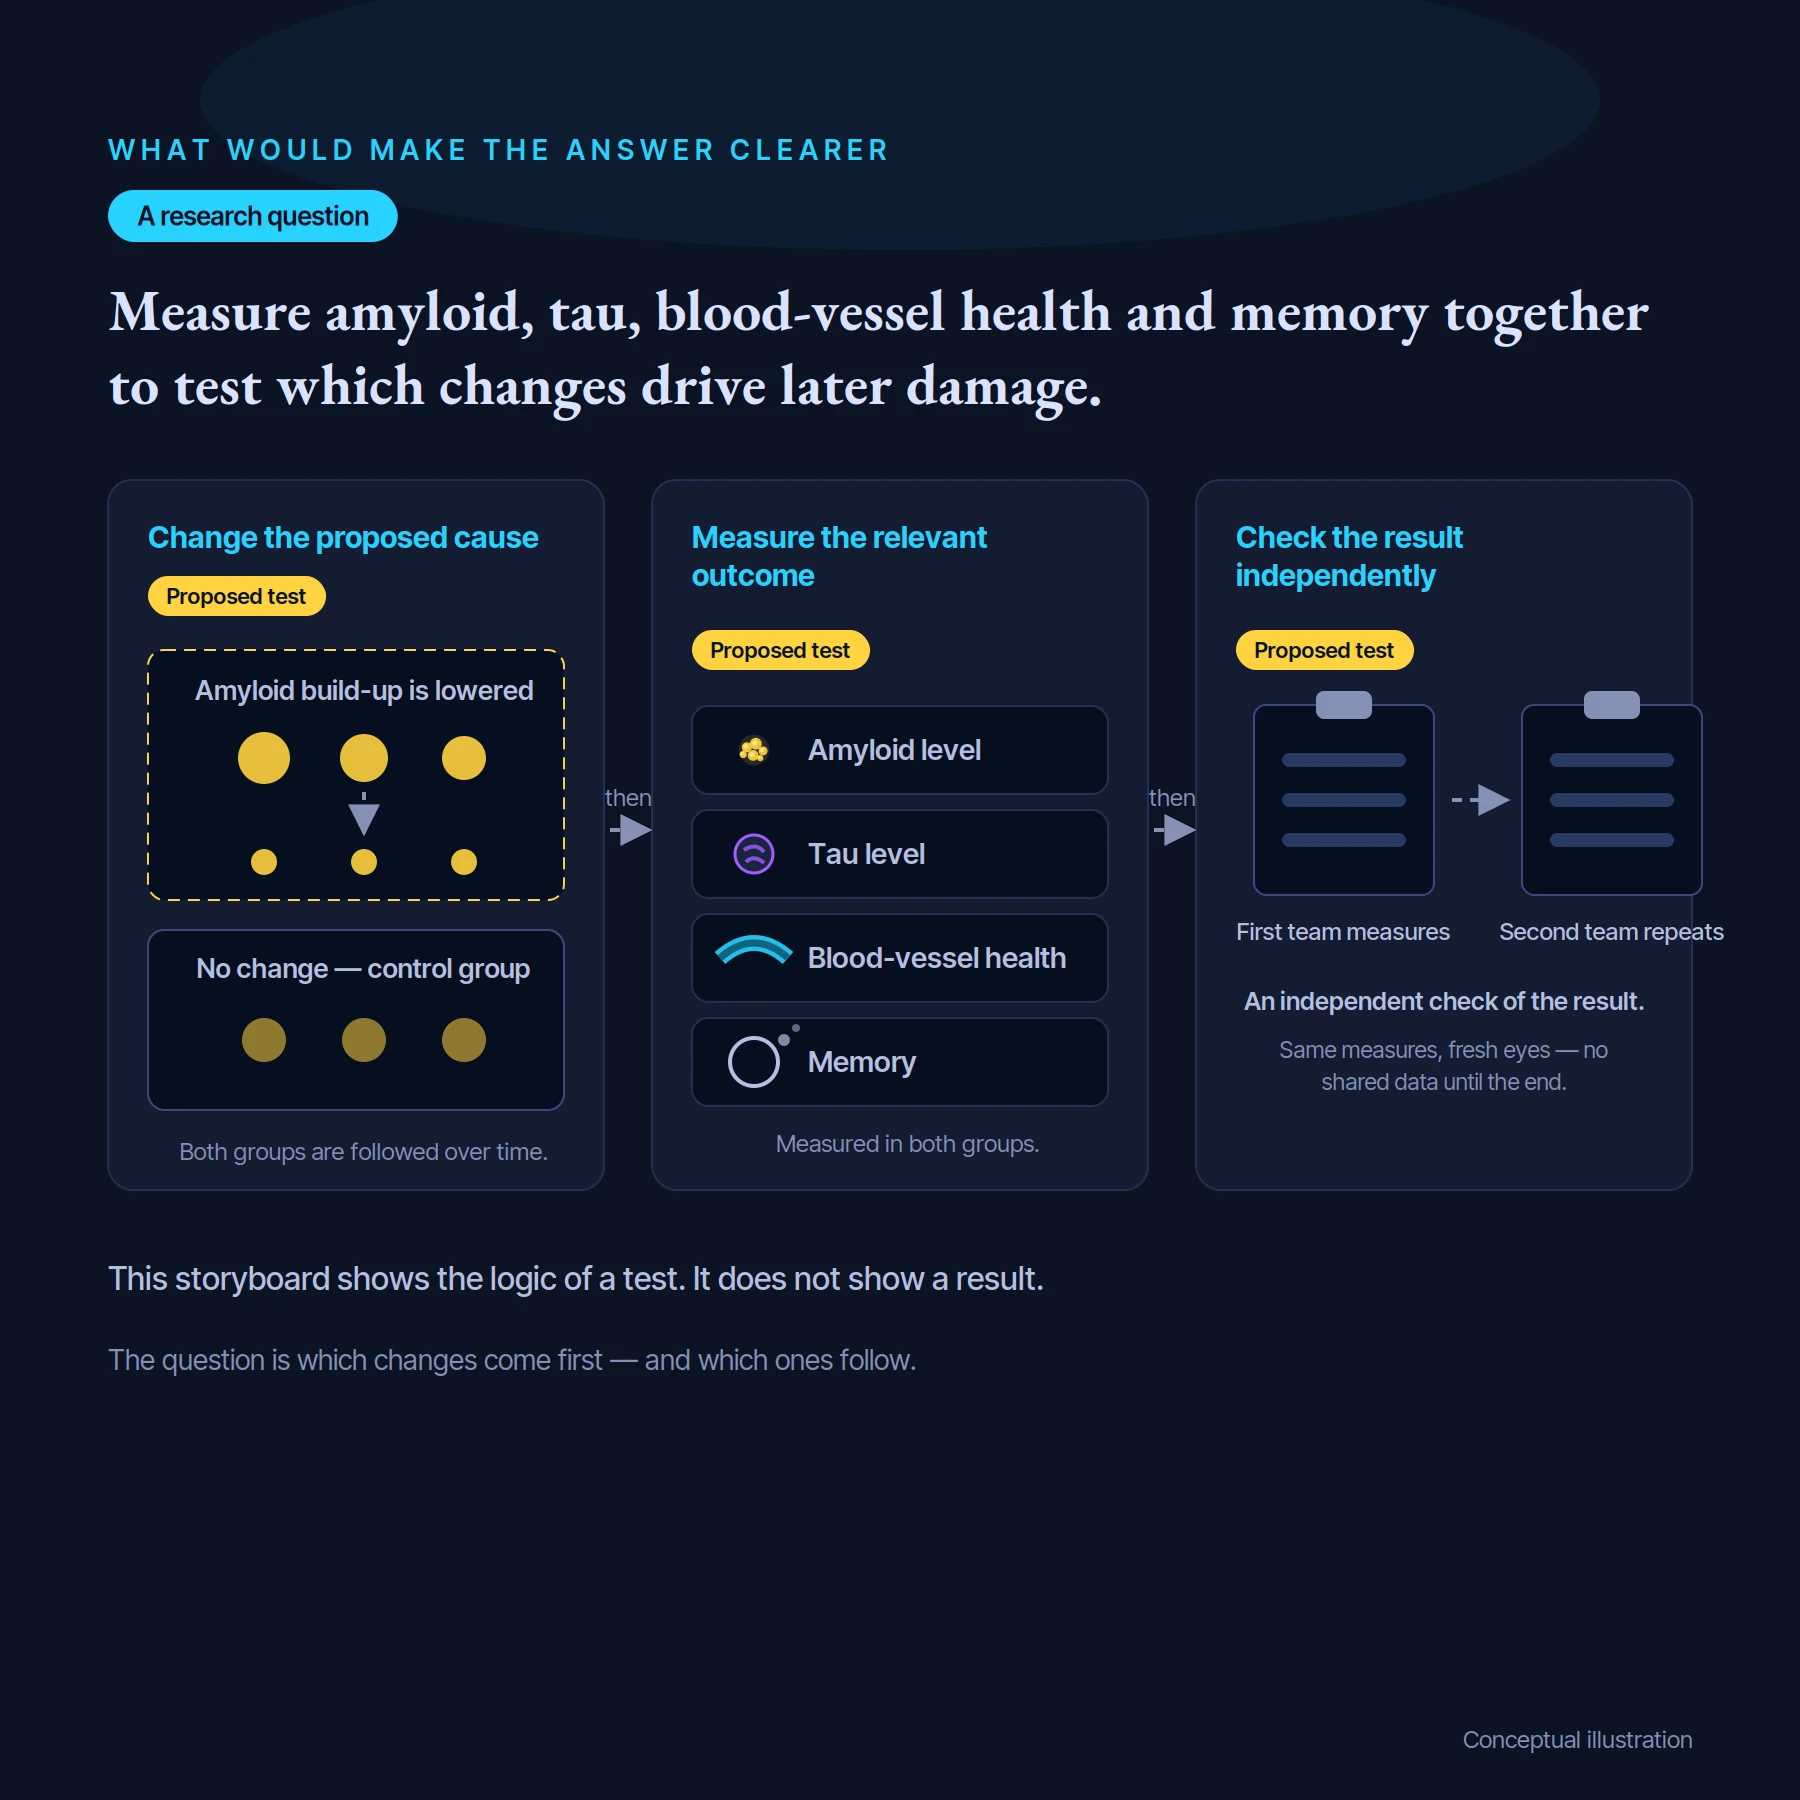
Measure amyloid, tau, blood-vessel health and memory together to test which changes drive later damage.
then
then
Change the proposed cause
Proposed test
Amyloid build-up is lowered
No change — control group
Both groups are followed over time.
Measure the relevant outcome
Amyloid level
Tau level
Blood-vessel health
Memory
Measured in both groups.
Check the result independently
First team measures
Second team repeats
An independent check of the result.
Same measures, fresh eyes — no shared data until the end.
This storyboard shows the logic of a test. It does not show a result.
The question is which changes come first — and which ones follow.
Conceptual illustration
Measure amyloid, tau, blood-vessel health and memory together to test which changes drive later damage.
Check that the intended change really happened.
Allow for other factors and compare with suitable controls.
Look for independent confirmation and the limits of the effect.
These are questions for research, not a claim that the proposed studies have already succeeded.
Proposed tests: 1 test design(s) are registered in the scorecard.
In plain terms, researchers would change the proposed cause, check that it changed as intended, then measure a meaningful outcome while controlling plausible alternatives. The result should be able to support or count against the claim—not only show that a pathway exists.
Study design: Randomize preclinical amyloid-positive participants to verified aggregate reduction with prospectively defined clinical follow-up, baseline tau/vascular stratification and blinded outcomes. Include a species-selective mediator contrast where feasible. Prevention of tau-linked injury and clinical onset would strengthen initiation; adequate sustained engagement with unchanged clinical onset would constrain it. Preserve non-Aβ APP/BACE functions and monitor harms.
What would be measured: Clinical onset/trajectory plus engagement and tau/vascular injury.
Important controls: Prespecified enrollment and follow-up; matched outcomes and substrate specificity.
Result that would support the claim: Consistent prevention with target engagement and causal mediator separation.
Result that would count against it: Adequate engagement without clinical prevention, or effect attributed to another mediator.
Follow the studies, detailed comparisons and evidence ratings behind this guide.
Open the scientific review →
