The question
Is low-grade inflammation the independent starting cause of ageing?
This is the specific idea being tested.
Is low-grade inflammation the independent starting cause of ageing?
What you need to knowInflammation can add to ageing-related damage, but is not established as an independent master cause.Relative explanatory fit: Alternative ranked ahead
Why the alternative fits better: DNA in the wrong place, injury and metabolic stress can activate immunity, which can worsen dysfunction.
Claim assessed: Chronic low-grade inflammation is an autonomous primary initiating driver of organismal aging rather than predominantly a consequence or amplifier of upstream damage.
Finding: The registered weakest-link bundle scores Β, bound by the observational age-relationship SC1. The causal-pathology sensitivity is Ζ and the primary-initiation sensitivity Γ. A bundle score is not a verdict that inflammatory biology is imaginary or causally inert.
Evidence scope: 69 primary reports; cutoff 2026-10-05; bounded critical review, not exhaustive systematic review.
The grade applies to the stated claim. Model rankings and individual subclaim grades remain separate from the overall causal-evidence grade.
Full scientific assessment and references · Scorecard (JSON) · Review source (Markdown)

THE MAIN FINDING
Inflammation can add to ageing-related damage, but is not established as an independent master cause.
The idea
Is low-grade inflammation the independent starting cause of ageing?
Low-grade inflammation
Ageing
Proposed chain — plausible, not established
What fits better
Best fit in this review
Damage and inflammation reinforce each other
Cell
DNA in the wrong place
DNA in the wrong place
Injury
Metabolic stress
Immunity activated
Dysfunction worsens
reinforces
Evidence settings
Laboratory changes
Animal outcomes
Human outcomes
A changed biomarker is not shown as a proven longer or healthier human life.
What remains uncertain
Which damage comes first in different tissues
How much harm runs through immunity versus direct damage
Whether lowering inflammation alone slows ageing in people
Laboratory changes, animal outcomes, and human health outcomes are separate kinds of evidence.
DNA in the wrong place, injury and metabolic stress can activate immunity, which can worsen dysfunction.
Conceptual illustration
This is the specific idea being tested.
DNA in the wrong place, injury and metabolic stress can activate immunity, which can worsen dysfunction.
A higher rank means a better fit to the evidence in this comparison. It does not prove every part of the leading explanation.
The reviewed hypothesis ranks 5 among 5 models compared; 1 alternative model(s) hold first rank for this stated claim.
Claim under review: rank 5 among 5 compared models.
Leading explanation: Damage-triggered immune reinforcement.
Position in this comparison: Last recorded rank.
The causal grade asks how well the stated causal claim is established. This comparison asks which of the assessed explanations fits the reviewed findings better. A leading explanation can remain unproven. Models can overlap or include the tested mechanism; an alternative ahead does not make that mechanism irrelevant. These ordinal ranks apply within this review; they do not measure the size of a difference or rank scientific strength across topics.
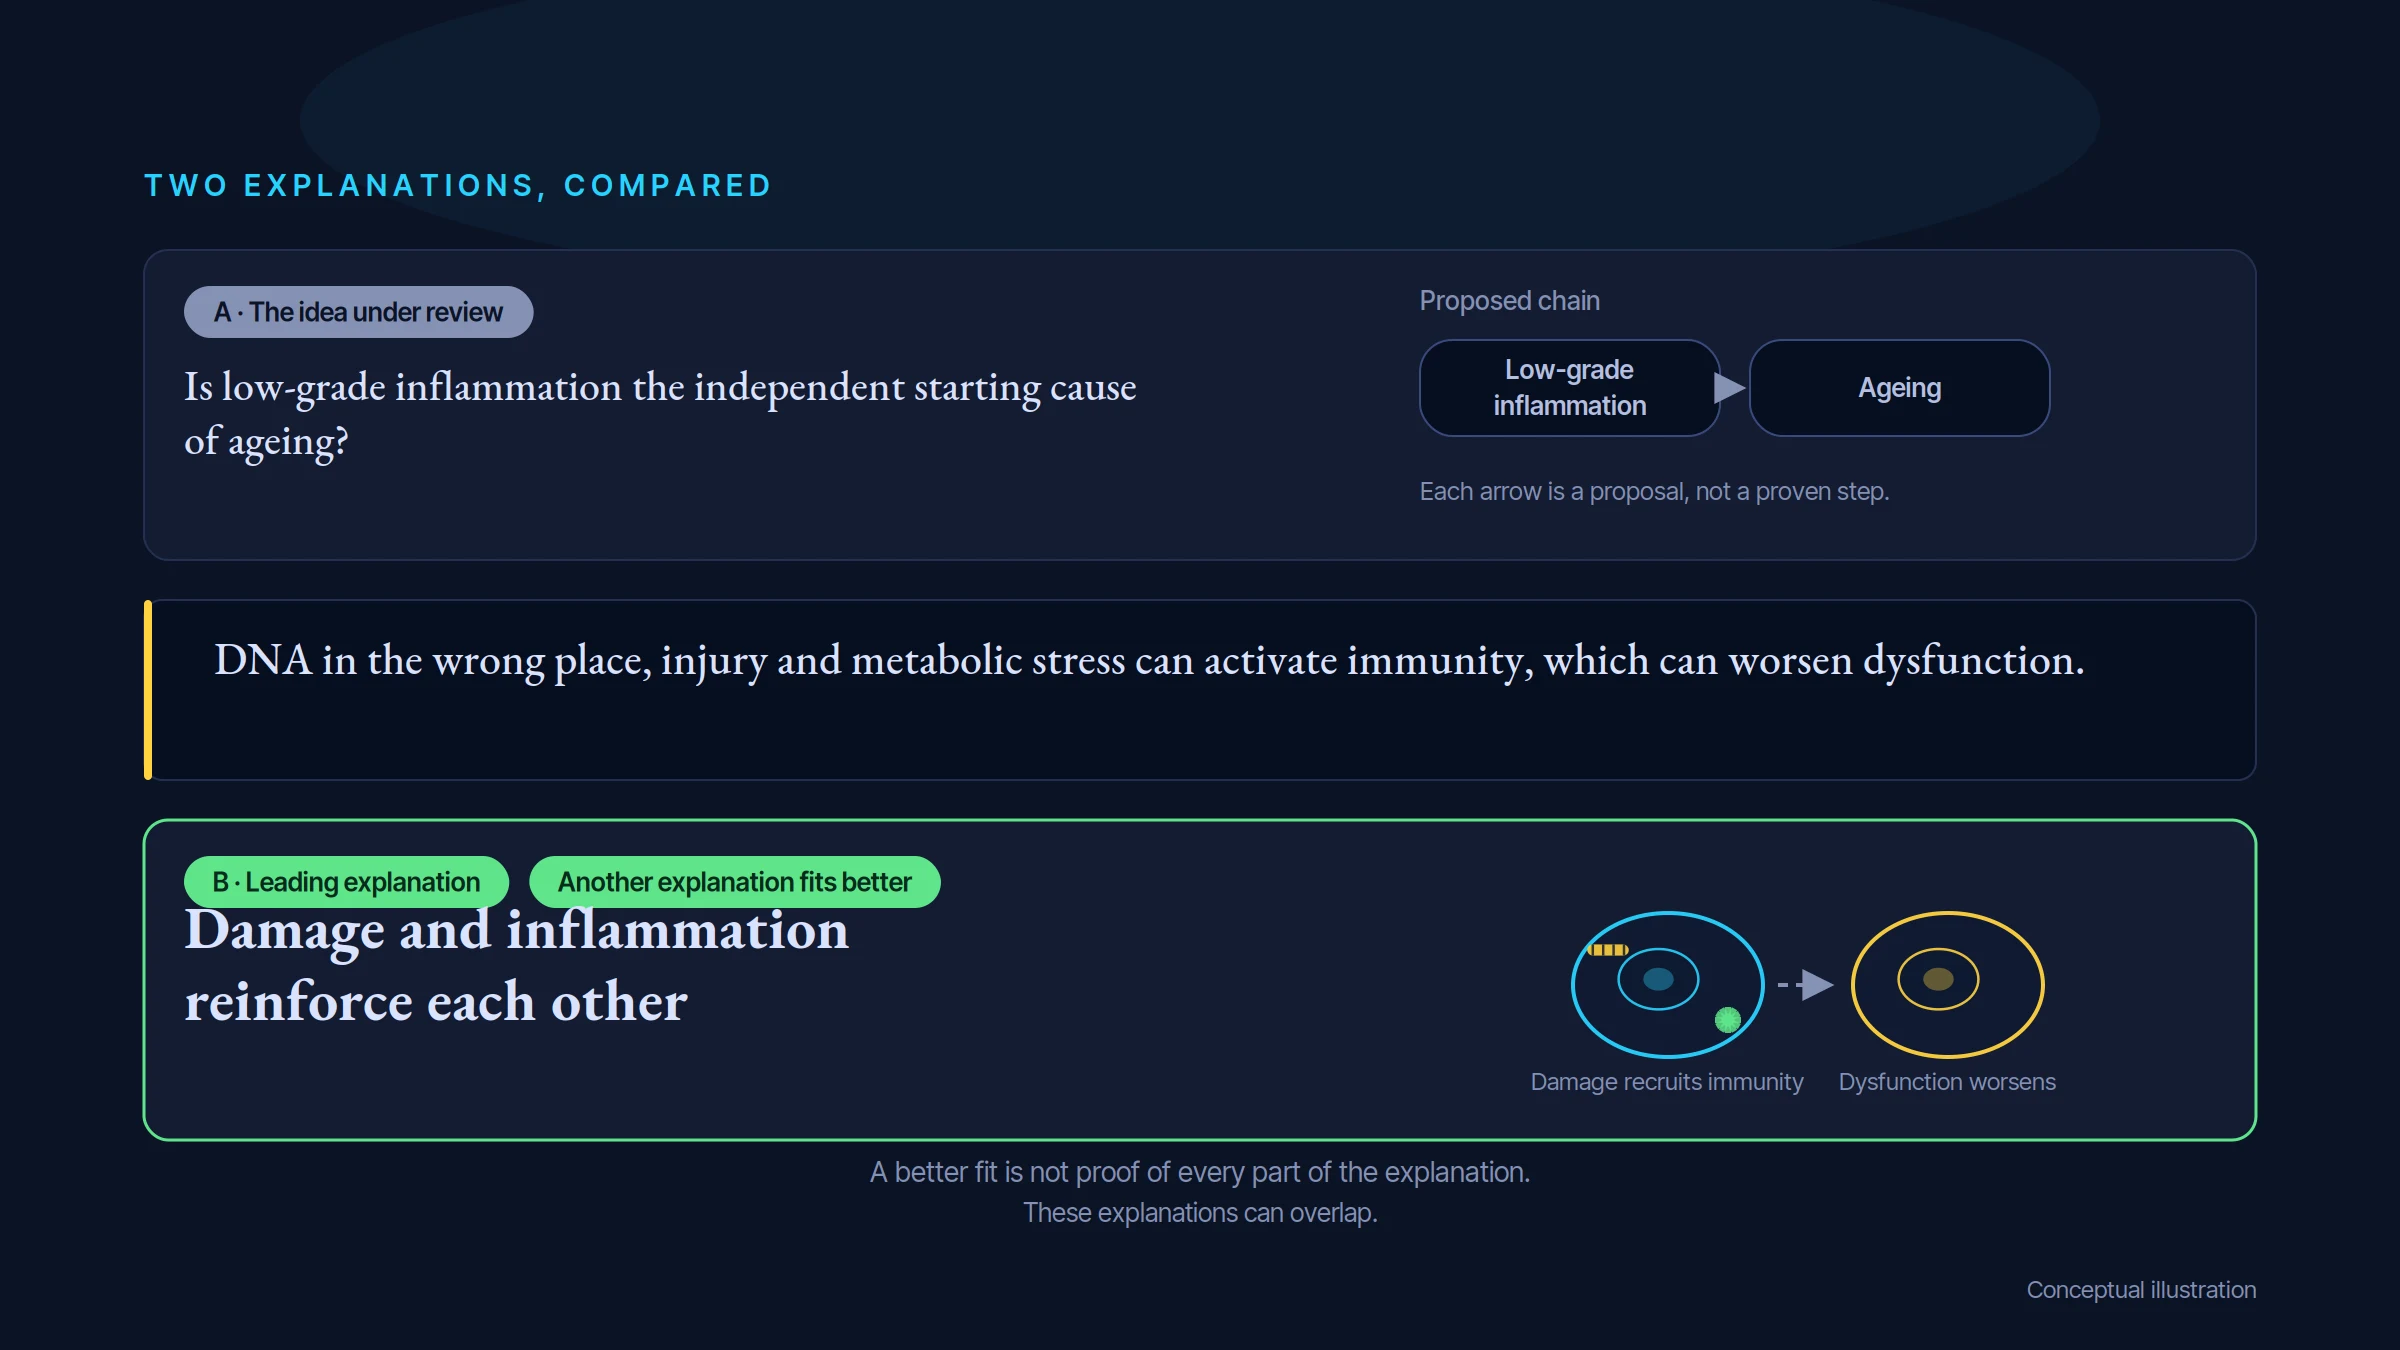
TWO EXPLANATIONS, COMPARED
A · The idea under review
Is low-grade inflammation the independent starting cause of ageing?
Proposed chain
Low-grade inflammation
Ageing
Each arrow is a proposal, not a proven step.
DNA in the wrong place, injury and metabolic stress can activate immunity, which can worsen dysfunction.
B · Leading explanation
Another explanation fits better
Damage and inflammation reinforce each other
Dysfunction worsens
Damage recruits immunity
A better fit is not proof of every part of the explanation.
These explanations can overlap.
Conceptual illustration
Association only for the stated claim.
DNA in the wrong place, injury and metabolic stress can activate immunity, which can worsen dysfunction.
These explanations can overlap. Ranking their fit to the evidence is separate from deciding how firmly a cause has been established.
Rank 1: Damage-triggered immune reinforcement — Misplaced DNA, injury and metabolic stress recruit immune circuits that feedback on dysfunction.
Rank 2: Senescence-origin signaling — Persistent stressed cells supply secreted or chromatin signals that propagate pathology.
Rank 3: Environmental and exposome contingency — Infection ecology, market integration and behavior shape inflammatory aging patterns.
Rank 4: Failure of resolution — Incomplete resolution and homeostatic immune support exacerbate tissue dysfunction.
Rank 5: Autonomous inflammation-first aging — Low-grade inflammation is the initiating central driver of normal aging.
Evidence rating: Β · Moderate confidence. How the evidence was assessed.
DNA in the wrong place, injury and metabolic stress can activate immunity, which can worsen dysfunction.
This is an assessment of a causal explanation, not proof that a particular supplement, diet, test, or treatment improves health. A treatment claim needs studies that test the intervention in people and measure meaningful benefits and harms. These findings can help frame research and informed clinical questions, but they do not identify what is right for one person.
Look for the proposed factor and the outcome, in the people or systems covered by the claim.
Damage and inflammation reinforce each other. DNA in the wrong place, injury and metabolic stress can activate immunity, which can worsen dysfunction.
Reduce defined inflammation while measuring the earlier damage that may trigger it.
These illustrations show the key questions tested in the review. They are conceptual drawings, not microscope images or experimental results.

WHAT WOULD MAKE THE ANSWER CLEARER
A research question
Reduce defined inflammation while measuring the earlier damage that may trigger it.
then
then
Change the proposed cause
Proposed test
Defined inflammation is reduced
Inflammation lowered
No change — control group
Both groups are followed over time.
Measure the relevant outcome
Earlier damage (measured first)
Inflammation level
Function over time
Measured in both groups.
Check the result independently
First team measures
Second team repeats
An independent check of the result.
Same measures, fresh eyes — no shared data until the end.
This storyboard shows the logic of a test. It does not show a result.
The question is which changes come first — and which ones follow.
Conceptual illustration
Reduce defined inflammation while measuring the earlier damage that may trigger it.
Check that the intended change really happened.
Allow for other factors and compare with suitable controls.
Look for independent confirmation and the limits of the effect.
These are questions for research, not a claim that the proposed studies have already succeeded.
Proposed tests: 1 test design(s) are registered in the scorecard.
In plain terms, researchers would change the proposed cause, check that it changed as intended, then measure a meaningful outcome while controlling plausible alternatives. The result should be able to support or count against the claim—not only show that a pathway exists.
Study design: Independent-site adult mammalian factorial experiment that blocks a defined inflammatory cell circuit before its rise, reinstates its mediator and crosses it with independently induced upstream DNA/mitochondrial damage; translate to a prespecified multi-year clinical function endpoint.
What would be measured: Time-resolved upstream damage, inflammatory engagement, multi-organ function and survival; patient disability or incident disease instead of a clock alone
Important controls: Cell-specific and drug-resistant rescue controls, developmental exclusion, exposure/background/sex replication, infection surveillance and blinded endpoint adjudication
Result that would support the claim: Selective pre-damage intervention prevents broad aging despite upstream lesion exposure and rescue restores it
Result that would count against it: Damage and aging proceed despite selective suppression or benefit remains limited to one disease endpoint
Follow the studies, detailed comparisons and evidence ratings behind this guide.
Open the scientific review →