The question
Does a more permeable gut independently start diseases elsewhere in the body?
This is the specific idea being tested.

Does a more permeable gut independently start diseases elsewhere in the body?
What you need to knowGut-barrier changes may worsen some conditions, but a universal initiating cause is not established.Relative explanatory fit: Alternative ranked ahead
Why the alternative fits better: Immune problems, diet or harmful exposures can come first. A changed barrier may then add to disease.
Claim assessed: Increased intestinal epithelial permeability is a primary initiating cause of human autoimmune, inflammatory and metabolic disease through translocation of microbial products.
Finding: Scope-matched SC6 returns Γ. The preregistered human cross-disease initiator has partial experimental support but lacks a selective causal test in its claimed scope. SC2 reaches Ε for mapped experimental contributions; it cannot carry the human initiation claims. Weakest-link would return Β because the descriptive association subclaim is Β; primary-subclaim and scope-matched return Γ.
Evidence scope: 68 primary reports; cutoff 2026-10-05; bounded critical review, not exhaustive systematic review.
The grade applies to the stated claim. Model rankings and individual subclaim grades remain separate from the overall causal-evidence grade.
Full scientific assessment and references · Scorecard (JSON) · Review source (Markdown)
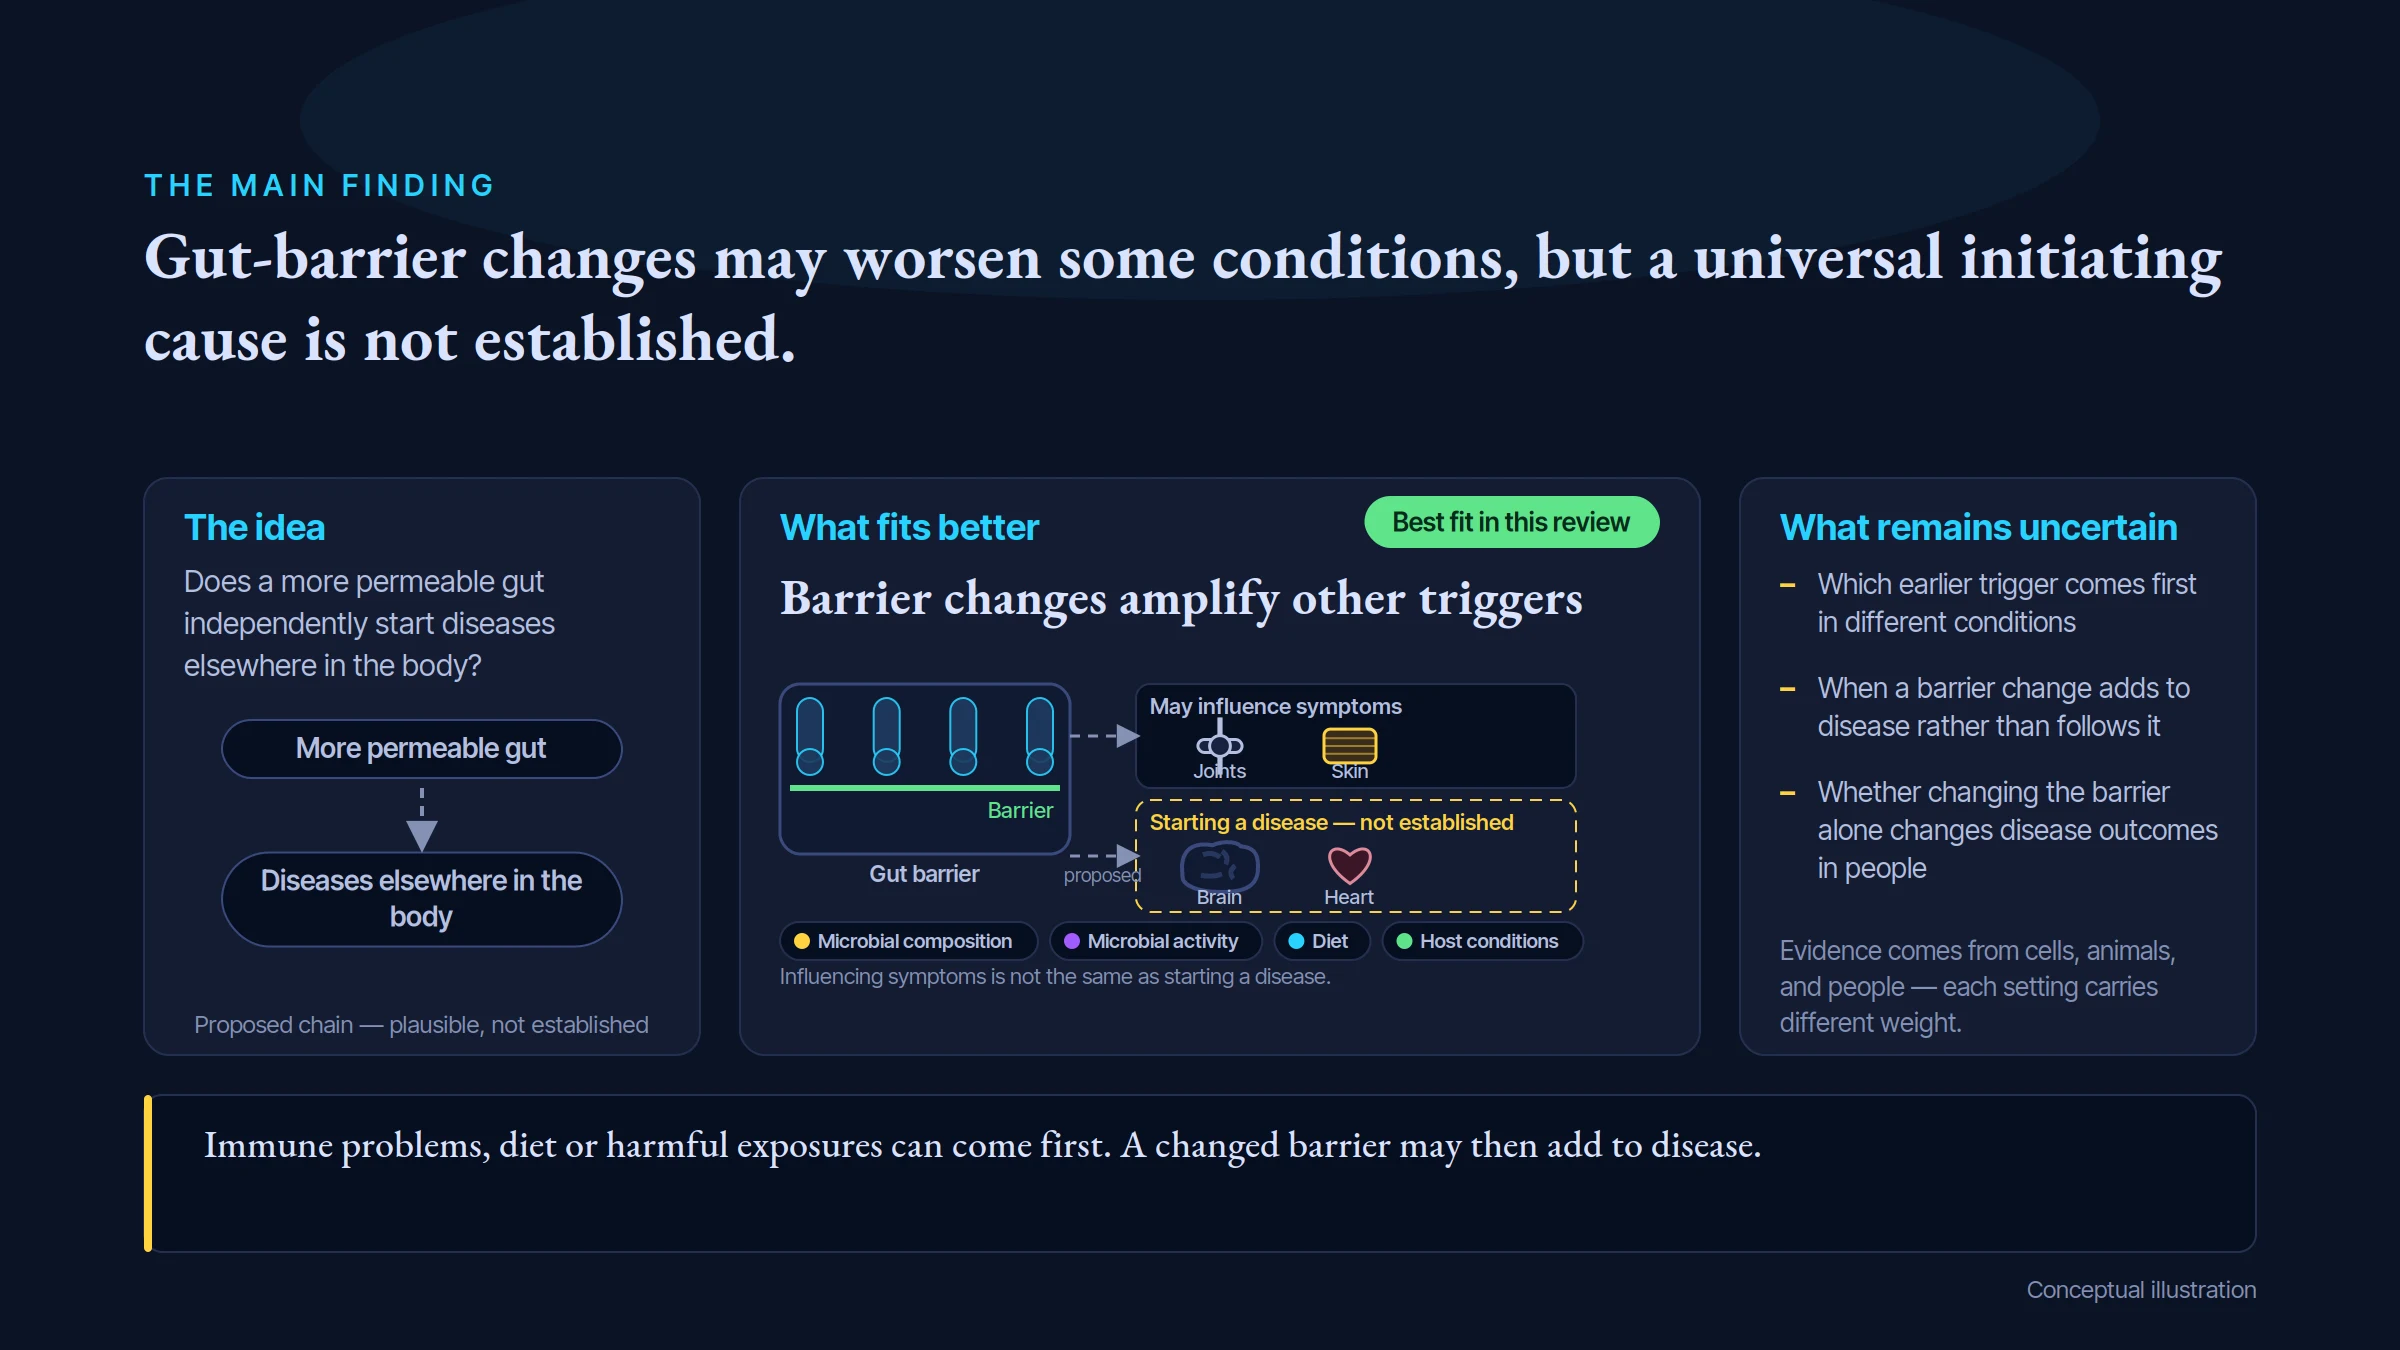
THE MAIN FINDING
Gut-barrier changes may worsen some conditions, but a universal initiating cause is not established.
The idea
Does a more permeable gut independently start diseases elsewhere in the body?
More permeable gut
Diseases elsewhere in the body
Proposed chain — plausible, not established
What fits better
Best fit in this review
Barrier changes amplify other triggers
Gut barrier
May influence symptoms
Joints
Skin
Starting a disease — not established
Brain
Heart
Links are proposed, not established
Microbial composition
Microbial activity
Diet
Host conditions
Influencing symptoms is not the same as starting a disease.
What remains uncertain
Which earlier trigger comes first in different conditions
When a barrier change adds to disease rather than follows it
Whether changing the barrier alone changes disease outcomes in people
Evidence comes from cells, animals, and people — each setting carries different weight.
Immune problems, diet or harmful exposures can come first. A changed barrier may then add to disease.
Conceptual illustration
This is the specific idea being tested.
Immune problems, diet or harmful exposures can come first. A changed barrier may then add to disease.
A higher rank means a better fit to the evidence in this comparison. It does not prove every part of the leading explanation.
The reviewed hypothesis ranks 5 among 5 models compared; 1 alternative model(s) hold first rank for this stated claim.
Claim under review: rank 5 among 5 compared models.
Leading explanation: Permissive second-hit amplifier.
Position in this comparison: Last recorded rank.
The causal grade asks how well the stated causal claim is established. This comparison asks which of the assessed explanations fits the reviewed findings better. A leading explanation can remain unproven. Models can overlap or include the tested mechanism; an alternative ahead does not make that mechanism irrelevant. These ordinal ranks apply within this review; they do not measure the size of a difference or rank scientific strength across topics.
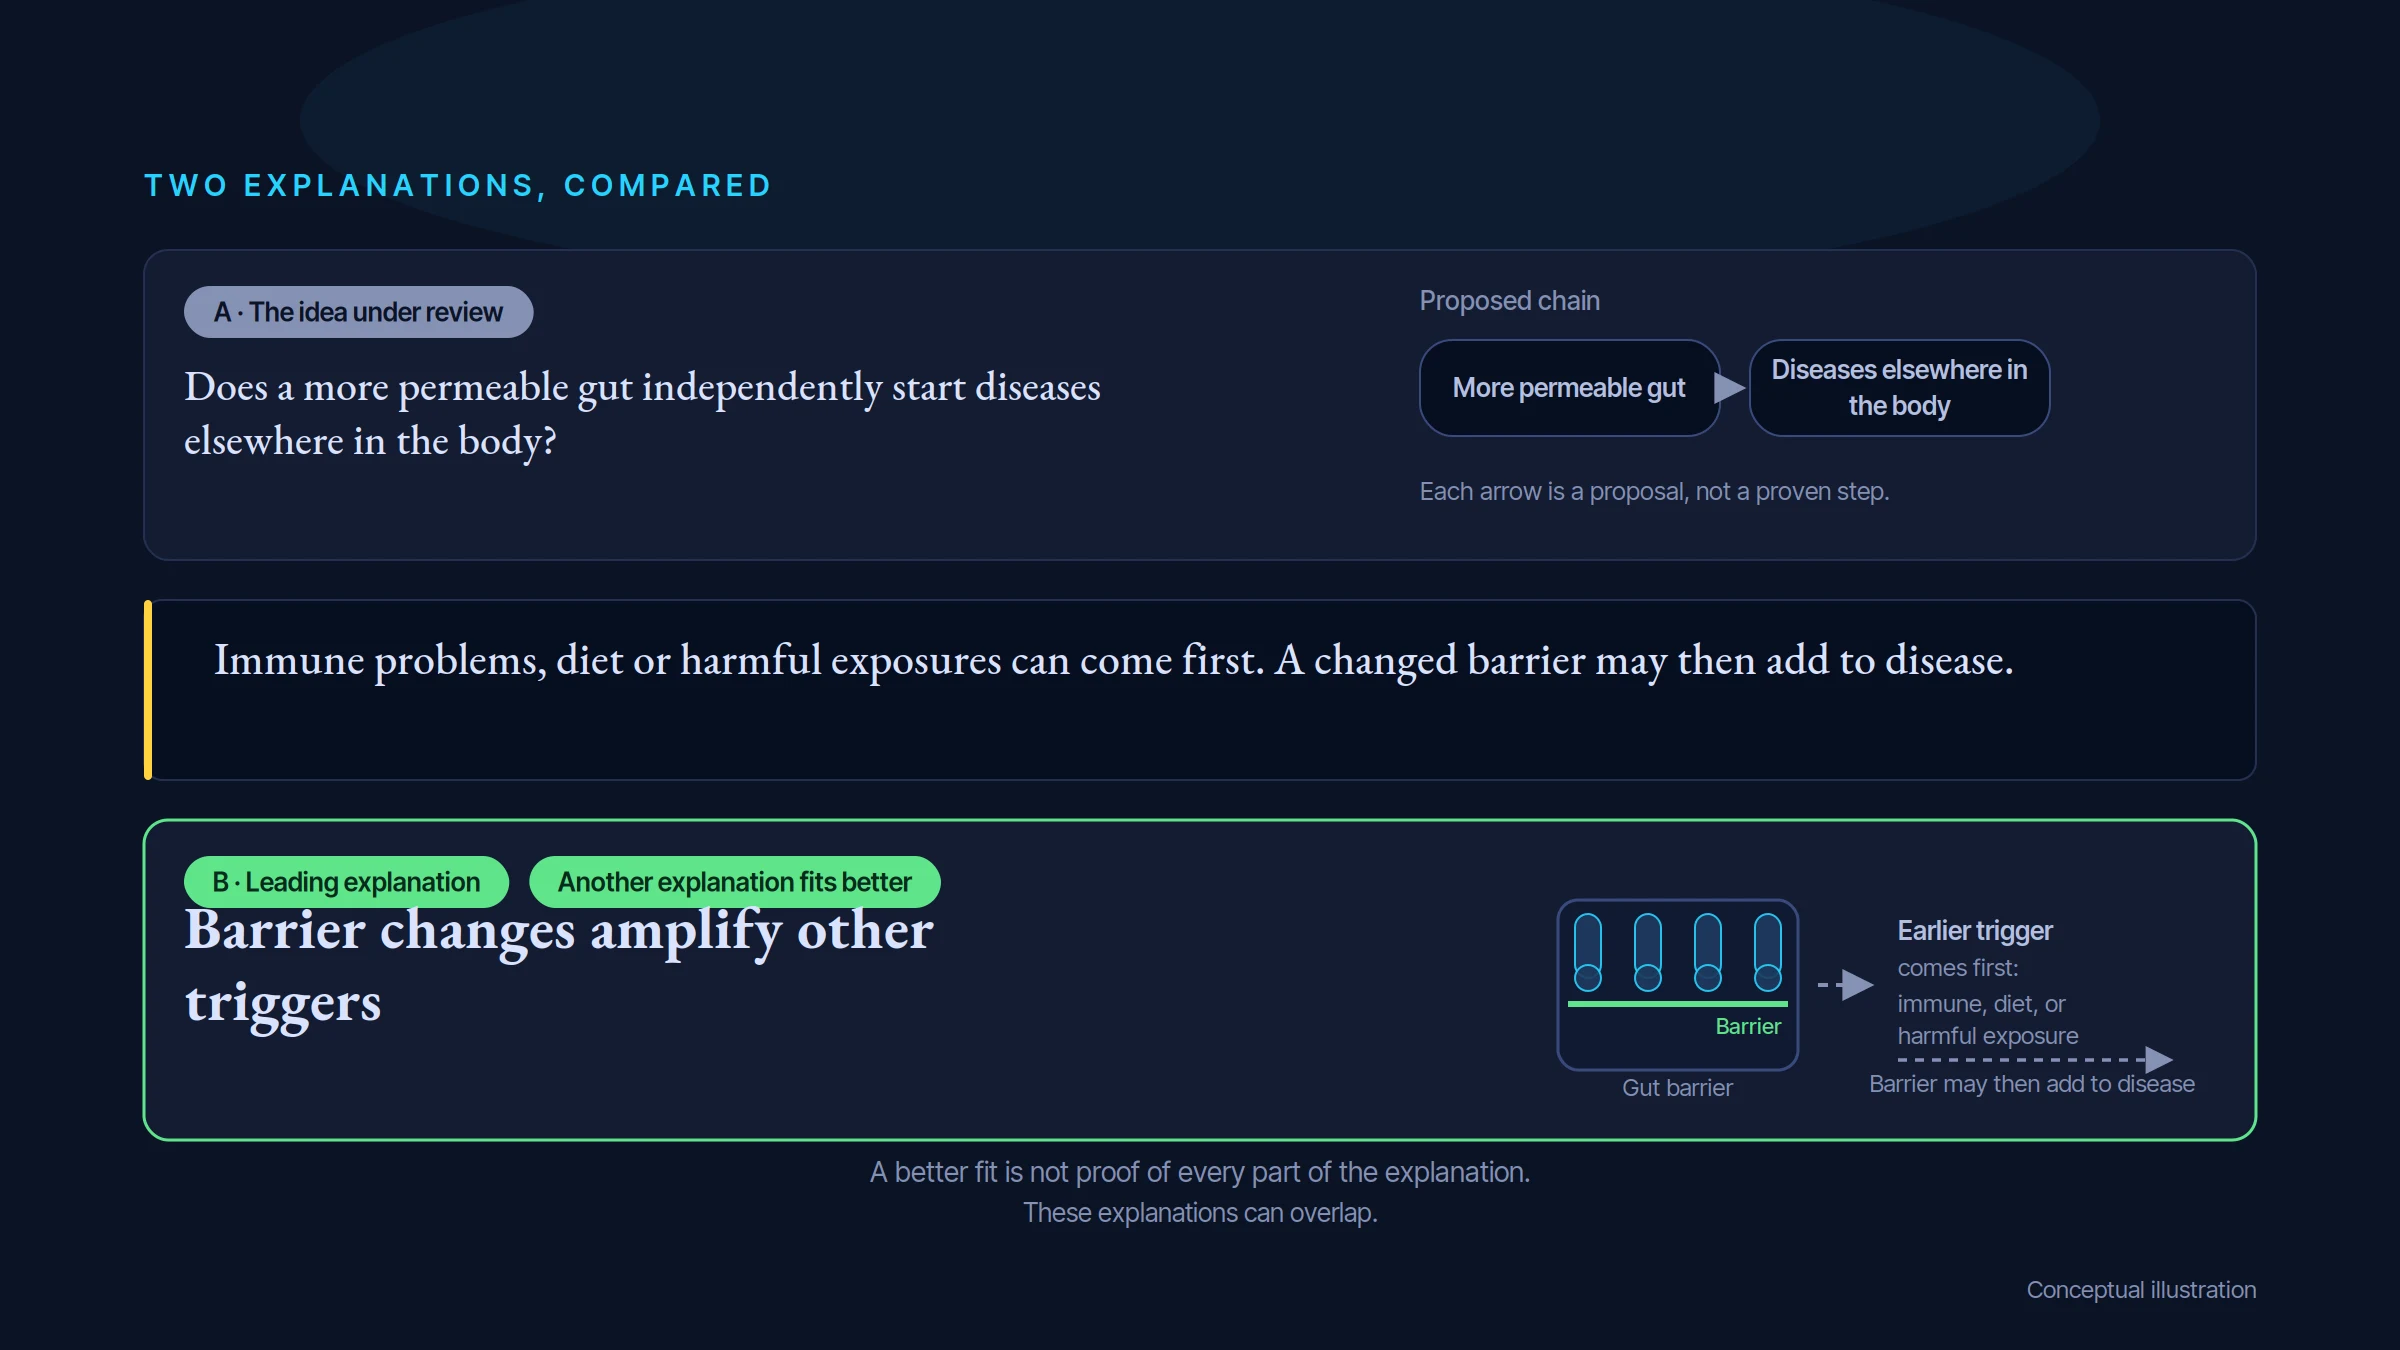
TWO EXPLANATIONS, COMPARED
A · The idea under review
Does a more permeable gut independently start diseases elsewhere in the body?
Proposed chain
More permeable gut
Diseases elsewhere in the body
Each arrow is a proposal, not a proven step.
Immune problems, diet or harmful exposures can come first. A changed barrier may then add to disease.
B · Leading explanation
Another explanation fits better
Barrier changes amplify other triggers
Gut barrier
Earlier trigger
comes first
Immune problems, diet or harmful exposures can come first
Barrier may then add to disease
A better fit is not proof of every part of the explanation.
These explanations can overlap.
Conceptual illustration
Plausible, not established for the stated claim.
Immune problems, diet or harmful exposures can come first. A changed barrier may then add to disease.
These explanations can overlap. Ranking their fit to the evidence is separate from deciding how firmly a cause has been established.
Rank 1: Permissive second-hit amplifier — An antecedent immune, dietary or toxic process makes barrier changes disease-modifying.
Rank 2: Multi-tier epithelial/vascular/hepatic firewall — Systemic exposure depends on successive containment and clearance layers.
Rank 3: Reactive permeability and shared diet/immune causes — Disease, glycemia or inflammation can cause leak and establish feedback loops.
Rank 4: Assay artifact in zonulin epidemiology — Some serum associations measure an unvalidated protein proxy rather than epithelial flux.
Rank 5: Permeability as primary systemic initiator — A common epithelial leak starts the assessed human diseases.
Evidence rating: Γ · Moderate confidence. How the evidence was assessed.
Immune problems, diet or harmful exposures can come first. A changed barrier may then add to disease.
This is an assessment of a causal explanation, not proof that a particular supplement, diet, test, or treatment improves health. A treatment claim needs studies that test the intervention in people and measure meaningful benefits and harms. These findings can help frame research and informed clinical questions, but they do not identify what is right for one person.
Look for the proposed factor and the outcome, in the people or systems covered by the claim.
Barrier changes amplify other triggers. Immune problems, diet or harmful exposures can come first. A changed barrier may then add to disease.
Change the gut barrier separately from the earlier trigger and measure disease outcomes.
These illustrations show the key questions tested in the review. They are conceptual drawings, not microscope images or experimental results.

WHAT WOULD MAKE THE ANSWER CLEARER
A research question
Change the gut barrier separately from the earlier trigger and measure disease outcomes.
then
then
Change the proposed cause
Proposed test
Gut barrier is changed
Barrier toggled
Earlier trigger: held separate
Unchanged in both arms
No change — control group
Disease outcomes are then compared.
Measure the relevant outcome
Barrier state
Earlier trigger
Disease outcomes
Measured in each group.
Check the result independently
First team measures
Second team repeats
An independent check of the result.
Same measures, fresh eyes — no shared data until the end.
This storyboard shows the logic of a test. It does not show a result.
The question is which changes come first — and which ones follow.
Conceptual illustration
Change the gut barrier separately from the earlier trigger and measure disease outcomes.
Check that the intended change really happened.
Allow for other factors and compare with suitable controls.
Look for independent confirmation and the limits of the effect.
These are questions for research, not a claim that the proposed studies have already succeeded.
Proposed tests: 1 test design(s) are registered in the scorecard.
In plain terms, researchers would change the proposed cause, check that it changed as intended, then measure a meaningful outcome while controlling plausible alternatives. The result should be able to support or count against the claim—not only show that a pathway exists.
Study design: Randomize objectively defined islet-autoantibody-positive participants or ACPA-positive pre-RA participants to a gut-restricted, selective barrier intervention versus matched control before clinical disease. Preregister flux and translocation mediation, disease incidence, follow-up and effect size; validate the agent’s target and independent off-target profile.
What would be measured: Incident clinical T1D or synovitis alongside validated size-selective permeability, microbial-product identity and longitudinal immune activation
Important controls: Equal diet and systemic immune therapy, blinded incidence adjudication, target engagement, an orthogonal barrier assay and prespecified baseline genotype/autoantibody strata
Result that would support the claim: Target-specific restoration precedes lower incident disease and mediation survives orthogonal perturbation and exposure controls
Result that would count against it: Verified restoration with adequate power leaves incident disease unchanged, or benefit is fully accounted for by systemic immunomodulation
Follow the studies, detailed comparisons and evidence ratings behind this guide.
Open the scientific review →
